Wednesday, September 28, 2016

Covering up on the beach


I was recently reminded of a media story concerning a young Australian woman who flew half way around the world to sit on a French beach wearing her Burka. The recollection happened whilst I was walking past Bondi Beach in Sydney where there was not a Burka in sight!


Aside from the reason for her international actions - which I am neither privy to or in a position to pass judgment on - I do admire her for "Covering Up" under the blue skies of a Mediterranean beach. I would however, challenge her choice of colour, black not being my first choice for a covering. In fact I suspect that she must have been gently simmering under the French sunshine. But if you go back several decades when Roman Catholic Nuns had no choice but to wear similar gear whilst administering to souls throughout the Australian outback. Not that wearing black was a health risk per se, just hellishly hot! Those Catholic Sisters actually succumbed to a more insidious killer that still remains a deadly scourge in many parts of the world - Typhoid!


But I digress!


Summer is almost upon us here in the southern hemisphere and we do need to re-visit the annual alarm over the devastation power of sunshine - not only in the form of Global Warming - but also upon our human skin!


Even if you have the "best" skin in the world when you're young, believe me, it will get old and you won't appreciate what the sun did to it in those earlier decades. THE SUN IS INCREDIBLY POWERFUL. It's the equivalent of thousands of Thermo-Nuclear reactions occurring every minute which are pumping out radiation that will destroy anything that falls into it's gravitational field of influence. Thankfully the Earth is in the Goldilocks position - not too close to fry to a cinder, and not too distant to freeze into an ice-block.


But just because the Earth "got lucky", doesn't mean that rubbing sun screen on your skin will protect you 100% against the sun's rays. It's like believing that airbags will save you in a high speed accident. They might reduce the harm, but 100%????


Avoiding direct exposure to the suns rays when they are most powerful is the best option. Don't expose yourself to the sun for more than a few minutes at a time between the hours of 10am and 4pm. If you do then make sure you're fully covered up with appropriate clothing (preferably not black), use high protection sunblock on any exposed areas, wear a broad rimmed hat and UV protection sunglasses.


Ampersands & angle brackets need to be encoded.

Saturday, September 3, 2016

What's white and makes your face itch? Answer: Dandruff.

I've been working out at a rural GP practice about 110km (about 70 miles) east of Perth here in W Australia. It's a great time of year to visit the country as the crops are coming up and the countryside looks FANTASTIC. Most people are saying that it's the best start to the farming season for 50 years. But not the farmers themselves - all they say is "have you seen the price of wheat? Gorn through the floor mate!" But then, have you ever met a farmer who's truly satisfied with farming .... until the money is in the bank!
Country folk are a great bunch of people, but they suffer the same problems as most other communities and they suffer the same kind of tragedies too.
One patient came in to see me and I immediately thought to myself that I've seen that face before!
In fact I'd never seen the person before in my life. What I had recognized were the obvious signs of Seborrhoeic Dermatitis. This presents as a classical flakey, itchy, red rash in the Naso-Labial folds of the face, in the eyebrows and often in the ears and on the chin too. (see my diagram below)
The cause? A fungal infection of the scalp that we often call DANDRUFF!
By using an appropriate shampoo, not only do you clear up the fungal infection but you cure the rash on your face too!
Talk to your GP about it: they'll know what to prescribe.

Ampersands & angle brackets need to be encoded.

Sunday, August 14, 2016

Hygiene for the outer ear


Small children and infants are often aware of their ears when they get a head cold and end up with an earache.

Many air travellers become aware of their ears as the aeroplanes gain altitude, or descend from cruising altitude when the cabin air-pressure changes and eardrums begin to "pop".

But most of us go through life never thinking about our ears until we begin to lose our hearing!

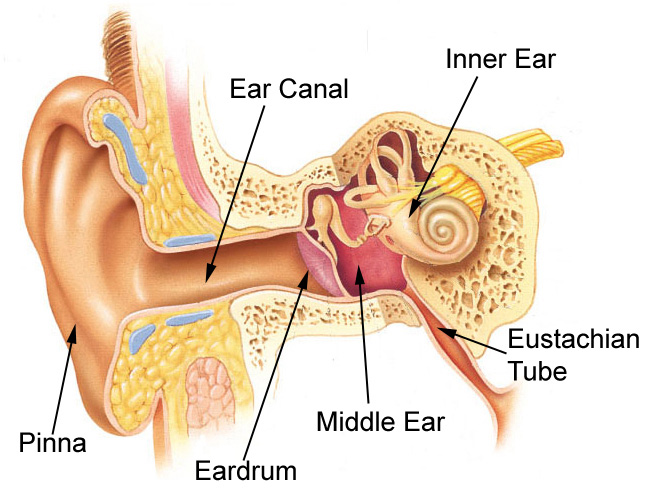
From the diagram above there are two main areas of the hearing apparatus (classically we talk about three, but who's going to be picky) The two areas are:


  • From the Pinna where many people hook their glasses onto, to as far as the ear drum.
  • From the Ear drum to the inner end of the Eustacian Tube which open into the back of the nose.


Today I'm just concerned about the hygiene of the outer part of the ear from the ear drum out. For some reason, people like to stick things in their ears, most notorious of all are cotton buds. Many's the GP and ENT specialist who's had to retrieve the end of the bud when it comes unstuck with the external ear canal. Hair grips are another villain of the peace. These metal instruments can end up scratching the lining of the canal and allowing bacteria to get to places where they shouldn't get.

Why do people stick things in their external canals? Mainly to relieve an itch they find difficult to scratch. Many of such people also have dandruff of other eczema like conditions. For those people I suggest a trip to the local pharmacy to buy a mild Cortisone based cream. By wiping some of this with a finger tip into the external canal you can relieve the itch/scratch cycle and then there's no need for anything else. If itching persists then visit your Doc to get some appropriate ear drops.

Another reason people use cotton buds is to dry their ears! For these patients I recommend using a Tissue Spear to gently dry the external canal. These can easily be made by twisting the corner of a piece of tissue or toilet paper and making it into  a pears shape. That can then safely, and gently, be pushed into the canal and help dry the contents. If you want a bit of extra "oomph" then use a hair dryer (on low power) held about half a meter away from your ear. (Make sure it's not on HOT as that can prove to be extremely uncomfortable).

But prevention is better than cure so if you don't want to get water in your ear when showering etc, then use a plug of Blue-Tack - it's works like a dream!
Ampersands & angle brackets need to be encoded.

Tuesday, March 29, 2016

Aussie Spiders - Reputation is worse than their bite!

Red Back Spider - Courtesy Sydney Morning Herald
My next door neighbour was telling me the other day that she'd been bitten by an insect on her foot. Apparently it "blew up" immediately and her Doc told her that she had developed cellulitis and started her on antibiotics.

A few thoughts stirred in my ageing brain, but I quickly moved on from the inappropriate prescription of antibiotics, to musing on insect and spider bites in this Great Southern Land called Australia. 

When the young bride and I first arrived down under we were regaled with stories of the most venomous snakes in the world, spiders the size of smartie with enough toxic venom in them to kill a horse - and all of these creatures are to be found in your backyard or under the toiler seat!! I also vividly remember a certain visiting Bishop develop a visible blood lust when called upon to deal with a large Tarantula which was holding court in our bathroom. The poor creature was drowned in Mortein by our Special Forces Prelate! I later learned to love those large, hairy arachnids who love nothing more than to dine on mosquitoes. Those buzzing, pesky insects, which can make an evening barbecue a living nightmare, are much more of a health risk than any spider is - just think Ross River Virus, Dengue fever ... even Malaria.

As far as spiders go Australia does have an impressive array of them and it's worth remembering that all spiders kill their victims (mainly insects) with a venom. But we shouldn't fear them as much as we do - apart from perhaps a couple of well known villains. Compared to we humans, even the most "dangerous" spider must be seen as veritable pussy cats!

Top of the list of "good idea to avoid" spiders is the Funnel Web.
Courtesy Australian Geographic
This is an aggressive little critter and if you think you've been bitten by one of these then you should pop along to your local hospital for prompt attention. The Neuro-Toxin they produce can have some very unpleasant side effects. The good news is that there is an anti-venom and secondly, no one has died from a Funnel web spider bite since modern first aid was introduced. In fact in the history of New South Wales only 13 deaths have been recorded.

One other spider you shouldn't poke a stick at is the Red Backed Spider - photo at top of the page. These lovely creatures live in a tangled we, are easy to spot and just enjoy eating other insects. Even the male of the species can be devoured by his mate in the course of mating (who said life is easy for we men?)
They certainly carry a huge punch but rarely leave their tangled fortress.

Problems occur when people/kids try to catch them, try to pick them up or think they are dead in the skimmer box of swimming pools. You will know if they've bitten you as the bite is very painful. Apply some ice, pop the offending insect into a bottle and head off to the local Hospital for the anti-venom. No one has died from a Red Back bite since the anti-venom has been available.

Here's a spider that has a lousy reputation for no reason at all! 
Courtesy Museum of Victoria
This is the White Tail Spider. It has a reputation of causing nasty flesh eating ulcers - but thankfully, the poor arachnid is seemingly innocent. In a study of 100 cases of identified white tail spider bites, not one of the patients suffered any loss of flesh!! Why devour a human when there are a billion flies to eat locally!

Just to put things in perspective:


On average:
  • Two people die from snake bites each year
  • Three people die from shark attacks each year.
  • Ten people die from Bee Stings each year.
  • Between 80 and 100 women die each year as a result of domestic violence
  • 1153 people died on the roads in 2014

There have been no deaths from spider bites since 1979
and there are far more spiders than humans out there!


Ampersands & angle brackets need to be encoded.

Saturday, March 19, 2016

Buying time with CPR - you CAN save lives!

I've just attended a 2 day workshop on Advanced Life Support and Advanced Trauma Life Support run by Western Australia's Rural Health Organization. Believe me, it was intense and hugely informative. I don't think I've pumped out that much adrenaline role-playing emergency scenarios in a long, long time! I came away with a greater confidence that even as a GP with nearly four decades of experience that I can do more to help the people I care for in emergency situations.

But there is something that everyone can do that can help save lives - CPR


Effective CPR buys time! Crucial time that allows an ambulance, or someone with a Defibrillator (and all airports, large urban shopping centres, gymnasiums etc now have them readily available) to arrive. Getting a Defibrillator onto a collapsed person who's not breathing - AS SOON AS POSSIBLE - provides that person with the maximum chance of survival.

Remember: maintaining circulation with CPR is the only tool we have when someone collapses outside of a hospital environment. And the big difference to survival is a DEFIBRILLATOR.

All Defibrillators are really smart machines: all you have to do is place the pads on the patients chest and switch the machine on. It will diagnose what's going and tell you exactly what to do.


So the message is simple:

  1. Learn effective CPR to buy TIME
  2. In the DRSABC algorithm you will learn, probably the most important thing to do is SEND FOR HELP which in real life is to say:

 "Call for an Ambulance and see if there's a Defibrillator in this place"

 You can make a difference. Effective CPR buys time, but a Defibrillator saves lives.
Ampersands & angle brackets need to be encoded.

Tuesday, February 2, 2016

Is there such a thing as Safe Sex?


Cunning little critters
"It's been going on since Adam was a Lad"  my dear old Mum used to say - sex that is! Talk to any (well nearly any)  hormonally charged young man or woman and they'd probably say it's the best thing on the planet. That was until mobile phones and virtual reality spoiled it all! For us of a more measured generation who are still used to answering/not answering land-lines, it's still way up there as one of the best experiences life has to offer.
The trouble with sex is, well, it really is THAT good and as a result advertising promotes the idea that the more you get the better it must be. Just think of all those boozey beer adds with beautiful young people eyeing each other off. They certainly don't look like they're heading to the library to study together. And I needn't mention those erotic adverts for what appears to be a jeweled ribbon appearing out of a model's buttocks and sold for a fortune as a 'thong' or 'G'string.
Selling bulk sex reminds me of why Vitamin supplements appear to be so popular. The promoters of such supplements appear to work on the idea that if a little is great to keep the human body healthy, then a Mega-Dose will be even better! Sadly, neither appears to be the case.
But back to sex. If it's so good then what could be wrong with it?
Call me old fashioned, but from my reading of the literature over the decades it seems to me that the safest/best sex is had in monogamous relationships and not by spreading it around with every consenting adult you can find. Why?

Because sex can be a real health risk!


  • Chlamydia - can make females sterile by irreversibly damaging their 'tubes'.
  • Syphilis - an ancient scourge that can even kill or send you mad!
  • Gonorrhea - another ancient scourge making a big comeback
  • Herpes - as one wit said "Not only love lasts forever - Herpes does too!"
  • Hepatitis B - can develop into a potentially life threatening disease.
  • Genital warts - now linked to the development of Cervical cancer and the target of a new vaccination program for young people
  • HIV - a sexually transmitted disease that has spread globally and still defies any cure


Then of course we must consider what coitus is also about - as well as all those nice fuzzy bits - the making of babies ... AKA conception.

If a male has vaginal sex with a woman there is always the potential for conception. Period (no pun intended)

This has been brought home to me in the last two weeks when I've seen one woman conceive who was on the pill and another who conceived who'd had her "tubes tied" 3 years previously! Believe me, those spermatozoa are devious little critters who will always find a way to a friendly egg.

So the next time you think about some recreational procreation/horizontal folk dancing or whatever the current epithet is, just beware that you may be leaving with more than just a happy memory - you may be changing your life (or someone else's) forever.
Ampersands & angle brackets need to be encoded.

Wednesday, January 27, 2016

Giving Hope to the Hopeless

I really wanted to write 'Hope-Less' because 'Hopeless' makes you immediately think that the person in front of you is a complete idiot. Whereas 'Hope-Less' suggests that they are devoid of nearly all coping mechanisms and have forgotten what hope really is. And believe me, that is a truly tragic state - especially when you see that lost look in a young kid's eyes.

It's vital we break the circle of despair

Otherwise we consign the next generation, and then the next generation to repeating the mistakes of their parent(s).

Most people are ignorant of what it's like to be in a situation where there is no job, your boyfriend has left you with 2 toddlers and run off with his ice addicted new partner. That your parents separated when you were young and you haven't heard of your father since. Or that your Mum's around, but what with the price of "smokes" and what's left of  the pension going on rent, food and medicines "she's not much help". And your so-called friends all smoke, most take drugs and most of them are pretty "hopeless" too. Yeah, you'd like to get away and make a new start but where do you go?

Believe me, in some areas of all countries that is the constant story seen by family GPs. That, and those who are on sickness benefits because of bad backs/depression/chronic pain ...who attend your surgery like a flock of worn out folk and each and every one of them looking 20 years older than they really are. Even the infants in their prams look confused at the behavior of the person who's wheeled them in on that particular day. 

Checking out their medical records you see a long list of anti-depressants: sporadic correspondence from psychologists/psychiatrist which start out optimistic and then segue into frustrated pessimism. These poor people find it so hard to change because every day they see and do the same things. As one person was heard to say: the definition of insanity is when you keep doing the same thing and expect a different outcome.

But the family Doctor is one person who can play a big part in their lives. These people attend our surgeries on a very regular basis. There is one treatment that we can give them which I suspect is one thing that they never get anywhere else - SELF RESPECT

Here's my suggestion: find time to tell these lost and damaged souls that they are worthy of our time, they do have value and they should learn to respect themselves even when other idiots try to put them down. I challenge some patients to do just one simple act - lift their heads and look up. Instead of seeing the rubbish and detroitus on the pavement, they'll see some trees, see the sky and maybe even hear a bird sing. It's only one little thing but if they persist it will become a habit ....  a habit of looking for HOPE. And dear God, some of these people need that in their messed up lives.
Ampersands & angle brackets need to be encoded.

Thursday, January 21, 2016

Your Secret Support - and how to improve your sex life!

We use it every day as soon as we get out of bed, and in fact many people use it when they're asleep too. It's one of the most neglected muscles in our body but when it fails to do it's job properly it can make our lives a misery!

I'm talking about the Pelvic Floor.

The pelvic floor is a sheet of muscles that support all the contents of our pelvis: which means -


  • The bladder
  • The rectum and it's faecal contents
  • and in women, the uterus and ovaries too


When the pelvic floor lets you down then controlling your urine can be a challenge when coughing, sneezing, straining or even just standing up! For those with loose bowel motions, a weak pelvic floor means that soiling your pants can be an embarrassing problem which may lead to social isolation as well. And when the bottom literally falls out of your pelvic floor, your uterus will often fall out too leading to a utero-vaginal prolapse!

Most of these condition are preventable by good personal care. For most people this means a lifelong approach to daily pelvic floor exercises and being aware of:

  • Avoiding constipation and/or straining with a bowel motion
  • Avoiding persistent heavy lifting
  • Treating chronic coughs and straining
  • Watching your weight and losing it if you're too heavy
So how can I improve the strength of my pelvic floor?

The first thing to do is to identify which muscles they are. After all, if you haven't used them for decades it's highly unlikely you know where they are in the first place! My suggestion is that the next time you go to the toilet to pass urine, try to stop mid-stream. When you do that, you're using your pelvic floor muscles and they are th emuscles you need to focus on.

Once you've identified them, it's time to exercise them. That's simple:

Squeeze and hold for 5 seconds and then relax - don't forget to include the muscles around your back passage too! Repeat for 5 slow squeezes and try to repeat three or four times a day. It's that simple and you can literally do these exercises anywhere and no-one will know what you're doing!

If you keep this up then after a few weeks you'll be aware that control of your urine will improve. And for ladies, as your pelvic floor muscles get stronger you'll be able to squeeze your vagina as well which brings me to the bit about your sex life .....
Ampersands & angle brackets need to be encoded.

Saturday, January 9, 2016

Beating the Drum for the Country Docs

It can be lonely out there


Rural Health - the real challenge.


As you may know, I took a few years off from clinical medicine as the emotional strain from caring for patients was hard enough, but running a practice was even harder! Now I've chosen to return to Family Medicine, but this time as a Locum GP, and I've chosen to help patients in the rural community. And it's been great!

Firstly, country people are different and have different problems. They're different in that they're more 'forgiving' and they're more thankful:  I had four 'Thank You' cards from one practice after just one three week Locum! But they face their own challenges too. Obesity is a big issue - excuse the pun - and is only compounded by the sense of inertia that occurs in small country towns. With the obesity of course comes Type II Diabetes with all it's insidious complications. 

Then there's a big issue with Chronic Pain Syndromes and the use of powerful analgesics that are being used to control them. It's a real challenge in such a short period of time to educate such patients on pain modulation, alternative treatments and the ancillary lifestyle modifications availabe. The resources needed are limited - professionals such as myself, clinical Psychologists and dieticians are nearly all FIFOs which makes continuity of care a real challenge.

And that leads to the one constant gripe of so many rural patients - with the inevitable question being asked "How long are you here for?" They feel that they are constantly having to repeat their stories to new faces (and despite computerised medical records, getting up to speed in 15 minutes in a complicated history is a tough gig even for someone with years of experience)  and many patients have literally given up trying merely limiting their consultations to requests for 'a new script'!

Our full time GP colleagues are bearing an enormous load in very isolating circumstances. I can fully understand why a female GP graduate with a young family would find it daunting to embark on a career in a remote rural practice. She would face so many professional and domestic stresses for which there are few practical answers. One may be to utilise the skills, knowledge and experience of those retired GPs who are looking for that something extra in life rather than playing bowls or embarking on another cruise, and developing an efficient, effective mentoring service!

Another would be to support groups such as the Australian Doctors Spouse Network that's been established to support Fellowship spouses in their un-ending merry-go-round of moving from hospital to hospital over their 6 to 10 year training. This group are aware of the challenges their partners face - perhaps Rural GPs Spouses can work with them to build support for their craft too.

Because at the end of the day, we're there to supply Health and Wellness information to our patients. We're there to support our patients when they're struggling. We're there to be their advocate when they have nowhere else to turn and to constantly remind them how special they are and why health is such a valuable commodity. 

At the end of the day it's all about our patients, and we can't do that properly unless we look after our Rural Doctors too.


Ampersands & angle brackets need to be encoded.

Tuesday, March 3, 2015

Thoughts on long distance air travel

Normally when we take to the air we travel from our home town of Perth in Western Australia and head West towards Dubai and Europe. This time we're going in the other direction and I'm actually typing these words, whilst I sit on the beach at Coogee NSW (and yes it's beautiful!). But tomorrow we continue our eastern adventure by taking wing to Los Angeles, a distance of 12,065 Kms or 13 hours flying time!

The biggest challenge for me is boredom. Flying tends to make one dozy anyway (and they keep turning down the lights to simulate nighttime) so actually being productive is always difficult. Once you've watched 3 movies in a row, the thrill of it beings to pall rapidly.

So I shall be taking a good book which I intend to at least open if not actually finish. I will take a notebook with me to record all those quirky things that happen when you're locked in with 350 total strangers (the good wife excluded of course)  in a metal tube at 37,000 feet, and I will get up and walk around as much as I can to stop the joints seizing up completely.

I usually start prepare for long distance travel some weeks before by working on my overall fitness and in the final week I try and do a little extra so that when I get on the plane my body will be craving sleep more than usual - despite the often cramped conditions back in "Stowage". Don't try and use alcohol as a means of getting to sleep, it will only make you feel lousy when you wake and will dehydrate you more too.

On the day of the flight I will put on my knee-length compression socks and wear them until I get into the shower at my destination. This is to reduce the risks of DVT's on such long haul flights. Because the air is drier at high altitudes I will take some lubricating drops for my eyes and some sesame seed oil to spray into my nose to keep those membranes protected to.

Once we're up, up and away then I'll drink plenty of water at regular intervals, get up and march up and down the aisles, and finally I do some stretches at the back of the aircraft - always designed to get some mystified looks from unsuspecting fellow travellers, or start up great conversations with fellow contortionists!

I also try to identify "coughers" - both in airports and on board - who may be infected with any contagious disease, by covering my face if they are near. I have also taken to wearing disposable plastic gloves when I use the communal toilet as the hygiene of others can sometimes be less than ideal.

After arrival and the obligatory shower, we go for a long walk before we go to bed and promise ourselves to be patient with each other for the next few days as the jet lag wears off.

But most of all I intend to have a ball in Seattle!

Ampersands & angle brackets need to be encoded.

Tuesday, February 24, 2015

The List

The young bride recently bought a kitchen blender which now sits proudly on our kitchen bench. It’s a wonderful machine and apparently does amazing things. I haven’t been allowed to play with it yet, but I have eaten of the fruits of the machine and they are definitely good!
Before she bought this blessed electronic gizmo, she made a list of everything she wanted from it. She then did a search of similar gizmos in order to work out which one was best for her. Finally she checked out Choice Magazine to see what they thought and where the best bargains might be found.
By now you might be thinking that I’m going to write about healthy eating. But I’m not. This is all about that strange and sometime scary event:


 “Going to see the Doctor”

From my early years when I was on the other side of the desk, to the more recent years when we've moved around to sit next to our patients, one of the 'heart sink' moments that we Docs all experience is the patient who comes in with the dreaded “List”!

Early on in life, a visit to the Doctors is usually a fairly simple  - earaches, sore throats, rashes, soft tissue injuries etc. But as we age and things start to creak and go wrong, then many people resort to “The List”. 

But beware, sometimes “The List” can end up being a double-edged sword especially if you leave your Doctor to decide which items on the list need his/her attention immediately. This is becoming more of a problem as most patients rarely get to see their own Doc these days. The reason being that most Docs are now part-timers who work in large clinics and they’ve probably never seen you before in their lives. All they have is you, your medical history and “The List”.

So my suggestion is to take a leaf out of the young brides book and do some “due diligence” yourself.

  • Make a list of all the things you want to talk to the Doctor about.
  • Prioritise that list with the things that you’d like to get attended to first.
  • Show your prioritised list to your pharmacist or Community Nurse to get their opinion. And if you’re a little nervous about it all then take an advocate along with you - family member or friend.

Be aware that if you have more than two things on your list it is wise to make more than one appointment to deal with all your issues. Believe me, one interview will never allow enough time to properly analyse multiple problems or to allow your Doctor to explain their thoughts to you.


Finally, if you think your Doctor is not giving you adequate time or failing to treat each issue seriously, then feel free to get a second opinion. 

Ask my young bride, if you were buying a food processor you’d look around for the best deal - so why not do the same for your life!
Ampersands & angle brackets need to be encoded.

Tuesday, February 17, 2015

NSAIDs - the debate that continues to inflame!


A good friend of mine, who just happens to be a retired medical man, recently fell and broke his hip. Nothing too unusual for a man in his seventies, but when we visited him in hospital he was furtively hiding his pain medication in a tissue and tucking it under his pillow. “It’s an Anti-Inflammatory” he confided conspiratorially The look of  confusion on my face prompted him to continue “They might be OK for pain relief but they interfere with bone healing and I want to get back on my feet as quickly as possible”.

I have to admit to always being a little nervous about using NSAIDs - Non steroidal Anti-Inflammatory Drugs - having studied medicine during the period when Phenylbutazone, the first proper NSAID, was introduced. BTZ, as it was popularly called at the time, was later discovered to cause bone marrow depression in many of those who took them and swiftly removed from “The Market” . 

But first a piece of history:

The fascinating ability to treat fever and inflammation dates back about 2500 (400 B.C.) years ago to a time when the Greek physician Hippocrates prescribed an extract from willow bark and leaves. Later in the 17th century, the active ingredient of willow bark Salicin was identified in Europe. Acetylsalicyclic acid (Aspirin), a more palatable form of Salicin, was produced commercially by Bayer in 1899. However, the mechanism of action of anti-inflammatory and analgesic agents such as aspirin, and its later derivative Indomethacin, were not discovered until the early 1960’s when medical science was really beginning to find it’s feet. Things really changed in the seventies, when John Vane discovered the mechanism of action of aspirin and other non-steroidal anti-inflammatory drugs (NSAIDs) opening the door to a pandoras box of new pharmaceuticals to treat pain and inflammation.

Since then the place of NSAIDs has become embedded in our lexicon of treatments for all things that involve inflammation and pain - especially those involving our joints. But the target tissues for these medications don’t just lie in our bones and joints, they are also to be found throughout the body in our stomachs, our kidneys, our hearts and our brains too. As time has gone by, the goal of Pharmaceutical Companies has been to develop medications that produce fewer side effects whilst maintaining their anti-inflammatory effects.

So what are the possible side effects of NSAIDs
  • Stomach ulcers
  • Raised blood pressure
  • Kidney Disease
  • Liver disease
  • Bleeding
  • Induce asthma attacks
  • Rashes, drowsiness, headaches

All of these side effects reflect the areas around the body that these medications have a collateral action upon, as well as the inflamed areas they’re principally targeted at.
A concern that I’ve had for many years is that some of these NSAIDs are now available “Over the counter” and are commonly used in children too.

WHAT I AM NOT SAYING IS THAT THESE MEDICATIONS ARE DANGEROUS AND SHOULD BE BANNED
rather

THESE ARE CHEMICALS THAT CAN HAVE SERIOUS AND SOMETIMES FATAL CONSEQUENCES IF NOT USED PROPERLY.

The vast majority of childhood inflammations and infections will settle without the use of medications. Common sense and patience are far better treatments than rushing to the Pharmacy for a magical “quick fix” - because that is exactly where those “quick fixes” should remain, in the realms of fantasy and fairy tales!

The human body has evolved brilliantly over the millennia to deal with minor injuries, minor illnesses and local inflammations. For major stuff you should always seek medical advice, because in most cases, Doctors do know more than you do.

But let me finish by saying that although Doctors know a vast amount about the human body, they are still far, far, far away from knowing everything. My medical friend with his broken hip refused his NSAIDs because he believed that NSAIDs slowed bone healing. Well, a thorough search of all the scientific papers written on the subject came to the conclusion:

“There is no robust clinical and/or scientific evidence to discard the use of NSAIDs in patients suffering from a fracture, but equal lack of evidence does not constitute proof of the absence of an effect. The majority of the available evidence is based on animal findings and these results should be interpreted with caution due to the differences in physiological mechanisms between humans and animals. ….. Till then, clinicians should treat NSAIDs as a risk factor for bone healing impairment and (they) should be avoided in high-risk patients.” 

ScientificWorldJournal. 2012; 2012: 606404.
“Do Nonsteroidal Anti-Inflammatory Drugs Affect Bone Healing? A Critical Analysis”
Ippokratis Pountos, 1 Theodora Georgouli, 1 Giorgio M. Calori, 2 and Peter V. Giannoudis 1, 3 , *

http://www.ncbi.nlm.nih.gov/pmc/articles/PMC3259713/


Ampersands & angle brackets need to be encoded.

Thursday, February 12, 2015

Hospitals make you better - don't they?


"Pyotr Petrovich admitted that he'd been a fool--but only to himself, of course.” 
― Fyodor Dostoyevsky, Crime and Punishment

There’s a good chance that you went to primary school with someone who ended up at Med School and is now a Specialist at something-or-other. You probably played together, got into trouble together or maybe you did/didn’t like him/her for any number of reasons. Then High School came along with different sports, activities, first dates, broken romances all the things that go with that decade of confusion.

The reason that I mention all this is because Docs are just like you and me - they’re human. At least I hope most of us still are! And being human we’re subject to good days and bad days, being brilliant one day and making mistakes the next. The only trouble is that when Doc’s make mistakes, it’s the rest of us who can end up in trouble!

In a  Swedish study from 2007, 12.3% of the studied population suffered an “Adverse Event” whilst staying in Hospital.  “Fifty-five percent of the preventable events led to impairment or disability, which was resolved during the admission or within 1 month from discharge, another 33% were resolved within 1 year, 9% of the preventable events led to permanent disability and 3% of the adverse events contributed to patient death. Preventable adverse events led to a mean increased length of stay of 6 days…. When extrapolated to the 1.2 million annual admissions, the results correspond to 105 000 preventable adverse events and 630 000 days of hospitalization".

Their conclusion: “This study confirms that preventable adverse events were common, and that they caused extensive human suffering and consumed a significant amount of the available hospital resources.”

Another study in Italy reviewed the case notes of 1501 patients who had been discharged from hospital. A part of their discharge summary recorded Adverse Events in 3.3% of those cases. Significantly less than the Swedish study, but still a huge number when extrapolated to the entire population of hospital patients over one year.

In Australia, the Australian Institute of Health and Welfare defines Adverse Events as “ Incidents in which harm resulted to a person receiving health care. They include infections, falls resulting in injuries, and problems with medication and medical devices. Some of these adverse events may be preventable”.

In 2011–12, 5.3% of separations (Discharge from Hospital) reported an ICD-10-AM code indicating an adverse event.

These figures are from our Health Care and Hospital systems where “Best Practice” is constantly being reviewed and updated, and where there are procedures for every conceivable situation. 

 Far from scaring people off from going into Hospitals, the message I am promoting today is:

 Never be afraid to ask questions of your Doctor or treating Medical team.

If you’re a bit overwhelmed by visiting your Doc or by being a patient in a hospital, then get someone to act as an advocate for you.

One final comment about my medical colleagues. We’ve all met those people who are arrogant and think they know everything. Or perhaps those who treat their fellow citizens with arrogant disdain. Well the bad news is that some of those went on to become Docs too! Thankfully, I’ve only met a few over my long career, but believe me, they are still out there. If you believe that your Doc has treated you badly, ignored your questions, not informed you of your treatment options or has just been plain rude - you are not powerless. Write a letter to the relevant Medical Board who are there to protect your interests. They are on your side and will not ignore your complaint.

The Caring Profession should be just that - The Caring Profession. Sometimes it doesn’t work to our advantage through no ones fault, but sometimes the Medical team can “drop the ball”. We are all part of the solution: we all need to make sure that we are responsible for our own health and that means daring to seek out information that will be beneficial to our long term health.

There should be no one on this planet more vigilant about your good health than YOU. In the case of those who need an Advocate, then take that responsibility seriously. Believe me, when Docs are patients, they are never afraid to ask questions of their treating team - because they know that things don’t always run as smoothly as the Hollywood image of Hospitals would have us believe.

95% of Medical stories have positive outcomes. But that’s not good enough. We are all a part of the solution.
Ampersands & angle brackets need to be encoded.

Tuesday, February 25, 2014

Stop calling me Skinny!


You’ll often hear it said that approximately 50% of the western world are either overweight or obese and that this can lead to serious health issues. And I agree with that. But I’m in the other 50% and am starting to get a bit fed up with being told that I’m getting skinny, or that I need a good feed to fatten me up.
Now, although I frequently write about the huge health threat that comes with obesity, what I do not do is go round telling people to their faces that they are fat and, why don’t they cut down on their eating.
The reasons behind this reversal of fortunes is that with so many people now being overweight or obese, half the population now think that their body image is normal and that the skinny ones are the abnormal ones.
As you all know, this year it’s 100 years since the start of that terrible first world war, and there have been lots of film footage of troops signing up and going to the front. So far I haven’t seen one fat person signing up in all that archival footage. Fair enough, smoking was more prevalent and cigarettes part of a soldiers rations, AND they did a great deal of marching up and down. But if they introduced conscription these days ( and heaven help they never do again) then there are going to need an awful lot of XXX large uniforms for over half of the troops.
Being overweight or obese is not the norm, but the pattern for it can so often be laid down in the first five years of life and that’s where we need to focus part of our efforts to fight the trends toward obesity related Diabetes, heart disease and cancers.


I was reminded of this after reading an article in the past on “Risk factors” for heart disease and in particular a study in the US which has been going on since 1972, and which has followed a community of people to study the incidence and causes of heart and blood vessel disease. This study, which is called the Bogalusa Heart Study and which has been an ongoing study for over 40 years now, has not provided any revolutionary results but some of the conclusions need to enter the mainstream thinking of every family, every school and every community.

But first a look at what we know, and you’ve heard it all a thousand times, but Smoking remains the No 1 bad guy when it comes to vascular disease - the type of disease that leads to heart attacks and strokes. Second comes Hypertension, or high blood pressure, which needs to be measured if you want to find out whether you have it or not. Then comes Diabetes, which if poorly controlled often leads not only to heart attacks and strokes, but also to disease of blood vessels supplying the legs, and when they get blocked gangrene and amputation may follow! And finally comes raised Cholesterol, obesity, age and being white - the Bogalusa study being run in a mixed biracial American community.

In this particular study the finding that neither obesity nor raised cholesterol rank highly as a risk will be of interest to the experts in those fields and will be the subject of intense, ongoing debate. But what we do know is that:

Since the introduction of ‘Statins there has been a 30% reduction in developing the risk for atherosclerosis - the plaque that leads to heart attacks and strokes. And that people with a Cholesterol level lower than 160mg/dL do not get heart disease irrespective of what their HDL, LDL cholesterol are or their Triglycerides are.
Obesity is linked with diabetes and diabetes is a significant risk for developing blood vessel disease. It is also linked to cancers and other medical problems and remains a real focus of necessary life style changes.

In fact one of the glaring outcomes of this 40 year old trial is that childhood nutrition and obesity should be the main focus of all preventative programs. If it’s left uncorrected then it’s linked to life long health problems that are not only physical but mental, educational and social too. So that’s why the childhood nutrition story needs to be told loud and clear and repeated in new ways year in and year out. If we give our children a healthy start in life then not only are they going to be able to make the most of their opportunities, but they are going to be healthier and get less disease. And what this means is that they are not going to need the services of our fantastic, but very expensive hospital services, which are paid for out of our taxes and our insurances. So the “price” of investing in getting our kids to eat healthy nutritious food is going to be a wonderful investment in their future and in our Nations too.

So where do we begin? Well in most places the machinery is already in place and beginning to work really well.

Smoking. Nearly every child I meet hates the smell of smoke, but sadly there are a great number of teenagers to take up the awful habit and unbelievably, cigarettes are still sold as Duty Free items in airports around the world. But in most developed countires, the good guys are wining and the percentage of smokers continues to fall, but we must never relent!
Childhood obesity requires serious, sensitive handling. Childhood obesity leads to a plethora of life long health problems. The key factors of teaching, showing, sharing better ways to eat need to be tailored to the individual and to be creative. The involvement of Chefs in school programs that allow children to try foods - and these are foods that they would normally “hate” -  prepared and presented in different ways so that the kids actually enjoy eating them, does have a huge impact. The widespread appearance of school vegetable gardens is another creative way of involving kids in making nutritious food choices and understanding how a healthy food chain operates..
Physical activity. Whilst not really impacting on weight itself, the direct benefits of physical activity in so many areas of life - heart disease, cancers, mood disorders and so on - mean that being active must always be an integral part of our education system.

Reducing risk is a lifelong health education challenge. We should not wait until mid-life to try and correct things that need not have occurred in the first place. So lets give our children the best tools available to build healthy lives, so that when their turn comes, then they will know how to build a great world for their children too.

image:
Ampersands & angle brackets need to be encoded.

Wednesday, February 19, 2014

To Sleep or not to sleep?


We all try and do it each and every night. Babies will do it for 20 to 22 hours each day and Teenagers seem to take to it like a duck to water. But for many people, trying to get a good nights sleep can be a challenge. Each year more than 5 million prescriptions are written in Australia, a rise of almost 9% since 2001. And a study released in 2011 found 95 per cent of patients who went to the GP to report an issue with sleep were given sleeping pills. These are very worrying trends and ones that we need to reverse as soon as possible. 

Recently, our nocturnal sleeping habits have been in the news because of the concern about the negative impact that these Sleeping Pills can have on our health. It’s been known within the medical community for many decades that giving sleeping pills to older people increases the risk of falls, confusion and the very real potential for serious interactions with other powerful medications that they take. But a report, released last year has now highlighted a possible link between taking these medications and premature death.
 
According to Daniel F. Kripke, MD, of the Viterbi Family Sleep Center at Scripps Health in San Diego, his study shows that (quote) “sleeping pills are hazardous to your health and might cause death by contributing to the occurrence of cancer, heart disease and other ailments." (unquote) In fact even those who reported taking between 1 and 18 sleeping pills in one year increased their risk of premature death by a factor of 3.6.

Their study is not only an interesting read, but it should sound alarm bells ringing within the wider community about the safety of sleeping tablets and why people need to take them. Despite the 2011 study findings about the ease with which sleeping pills appear to be prescribed, in my experience, most people within the medical profession treat sleeping tablets with the
respect and will generally only prescribe them when the benefits of using them outweigh the potential harm that they may cause - and then only for a very short course too. But for many with sleep disturbance there are usually some other underlying issues that need to be looked at such as:
Depression
Pain
Stress and anxiety 

All of which need to be attended to before one reaches for the sleeping pill bottle. The challenge here is that if you’ve missed several nights sleep, the benefits of a long term sleep hygiene program seem less attractive than popping a pill to get you to sleep that night - hence the emotional pressure on the treating doctor to use short term hypnotics as an aid to achieving a longer term, non sleeping pill associated goal. 


But another article which intrigued me from the New York Times, was on the subject of what is “Normal Sleep”? Because if we can’t define normal sleep and pass that onto our patients, then many people may ask for help when, in fact, they are having a “normal” nights sleep.

The article was based on the work of the historians Ekirch (2005) and Koslofsky (2011) who propose the theory that before the Industrial Revolution, segmented sleep was the normal pattern. In these pre- industrialized times there were two distinct sleep phases that were bridged by a period of wakefulness. In fact, during this wakeful period people used the time to reflect and pray: for the tired labourer who went to bed “dog tired”, this was the time that they usually had sex: and for the poet and writer these early hours were often the most fruitful as they were able to write uninterruptedly.
Some people used to get up and visit the neighbours and of course, it was also the time when the “bad guys” went and did their evil deeds!

Today, there is sound scientific evidence that a midday nap associated with nighttime wakefulness is associated with greater alertness than with the “mono-phasic” sleep-wake cycle - or a straight eight hours.

According to Eklrcks theory, it was the introduction of street lighting that allowed people to stay up later, and that, coupled with domestic lighting, started the trend to longer social evenings. With longer evenings came the idea that an eight hour sleep should be the “norm”. But according to Erlick there are abundant references throughout literature that refer to “first sleep” or first waking, with examples to be found in Shakespeare, Homers Odyssey as well as many personal records of lay persons who were able to write in centuries past.

If Erlick and Co are correct in their assessment, then I would suspect that millions of people will take a big sigh of relief and realize that their sleep patterns are “normal” after all.

In this 21st century of ours we like to have everything neatly packaged and labelled so that we have a feeling of control - and for many millions of people, this applies to their work/play/sleep cycles too. If there is one thing that sleep and dreams teach us, it’s that in the sleeping state there is no control and that we still have so much to learn about what sleep actually is and what dreams are.
 
For those who would like to improve the quality of their sleep, then my suggestion is to try to improve your sleep “hygiene”. So here are a few tips taken from the Mayo Clinic that I hope will enhance your quality of sleep over the months ahead.

  • Stick to a sleep schedule in other words. try to go to bed at around the same time each night.
  • And if you're not sleeping Give yourself 20 minutes and Get out of bed. read a book or magazine until you are sleepy and then try again.
  • Avoid the temptation of trying to sleep when you can’t. The frustration this causes will only make you more alert
  • Use your bed and bedroom for just two things: sleeping or sex. PLEASE, no TV or computer screens in the bedroom.
  • Find ways to relax. A warm bath before bedtime can help prepare you for sleep. Having your partner give you a massage also may help relax you. Create a relaxing bedtime ritual, such as reading, soft music, breathing exercises, yoga or prayer.
  • Try and take your Exercise and physical activity. at least five to six hours before bedtime.
  • Avoid or limit caffeine, alcohol and nicotine in the evening. 
  • Avoid large meals and beverages before bed. 
  • Check your medications. Especially anti-cold and flu medications.
  • Don't put up with pain. See your Doc.
  • Hide the bedroom clocks. The less you know what time it is at night,
    the better you'll sleep. 

     Happy dreams
!
Ampersands & angle brackets need to be encoded.

Wednesday, February 12, 2014

SME's and the future of Health Care in our Communities


TRANSCRIPT

It’s been almost imperceptible, and yet it’s been quite dramatic. I’m not talking about the Internet, Facebook or even Twitter, although they have played a significant role in the social changes that we see and read of, each and every day.

I’m talking about Health Care.

Notice, I’m not talking about Sickness, Disease or Accident care, but about Health Care.
Now …
If you were to time travel back to the post war period in any western country, you went to the Doctor because you were sick. The Doctor would invariably know your Mother and your father and may even have brought you into the world you at the local hospital or perhaps at home. And if you were really sick that Doctor would almost certainly have visited you in your own home … and probably stayed on for a cup of tea too. However it wasn’t all Nirvana back then in GP land, because in all likelihood, your Family Doctor would have sat at the side of your bed smoking a pipe - but I digress.

Over the ensuing decades, with the massive increase in technology that was associated with medical diagnostics, plus all the paramedics that are vital to the normal running of our current Health Care systems, the cost of providing health care services has sky rocketed. So the emphasis on so-called Preventative medicine became the norm, with the logical precept that if you reduce risks for certain chronic medical conditions - such as Heart disease, Diabetes, Cancer and many others -  then the savings accrued would reduce the future burden of burgeoning health care costs. And we’re talking of billions of dollars here.

So it became the norm for GP’s to promote Preventative Medicine as the way forward, as they were seen to be in the ideal position with their knowledge of medicine and of their patients. But then two invisible forces began to collide.

The time it takes to action many of these preventative screening programs started to eat into the time that the GPs actually had to see sick patients. Because not only did they have to go through a particular screening process, they then had to document it all. All of which does not fit neatly into a 15 to 20  minute standard consultation.

Secondly, GPs had stopped visiting patients in their homes. And because so many GPs were now part-timers, continuity of care was rapidly disappearing too. That has led to the current situation where many time poor GPs do not know the social or family history of their patients, apart from what the previous treating GP had written in the patients electronic notes.

Pity the poor patient then who has a high fever and needs to get back to work as fast as possible, but can’t get in to see the Doctor for 3 or 4 days because the Doctor is “Booked out”. And when they do get an appointment, they are often left sitting in a crowded waiting room where cross infection is a real possibility.

The challenge as I see it is to get GPs to see those who need a Doctor - the sick people of our communities: and to create an environment where people can access real Health Care in the places where they spend most of their time - the places where they go to work.

People will visit the Doctor maybe two or three times a year, but they will often see a different Doctor each time. Those same people go to the same workplace up to five days a week for about eight hours each day: in fact they actually live and work in a little community. And its inevitable that after a period of time, each persons family and social history is known to their fellow workmates.

Today most, if not all large corporations will be offering a whole range of healthy living programs to their staff, because they know that it’s an investment in their most vital resource - the people who work for them - and in nearly all those cases this investment in their staff also helps the financial bottom line too.

However, over 90% of the National Workforce work in small to medium sized enterprises - or SMEs - and the vast majority of these do not have the resources or the skills to enact Healthy living programs for their limited staff numbers. There is no doubt that some employers would see such intervention programs as an extra headache, and it may be that some staff would even see it as a threat. But the benefits of creating a healthy work environment and encouraging the employers and employees to live a healthy lifestyle too, are not just limited to the SMEs themselves. International reviews suggest that it could have far reaching economic benefits for the wider community as well. Dame Carol Black, National Director for Health, Work and Wellbeing, in the UK has calculated that improved workplace health could generate cost savings to the British government of over £60 billion – the equivalent to nearly two thirds of the NHS budget for England. And these figures would no doubt be somewhat similar all around the developed world.

Thus it seems logical for people who are sick to be seen by people who are trained to investigate and treat people who are sick. And it would also seem logical that businesses who need healthy workers to operate efficiently, should be committed to promoting healthy lifestyle for those workers.
The spin offs from such initiatives would include

Better health for the national workforce - in other words the vast majority of the population - with reduced risk of chronic health issues.
More time for Doctors to do their “Doctoring”
Massive savings in the future for the Health care industry allowing scarce Health care dollars to be targeted at areas of most need.
Significant savings for businesses who promote healthier workers: and the reputation of being seen as an employer of choice who cares for their employees.

So how does this work?

Firstly each SME needs to identify the needs of their particular business. Hairdressers would have different needs to a plumber and a car mechanic would have different needs to an office worker, so some basic data collection is needed before any thought to a particular program is started.

Once this data has been collected and a health care initiative identified, then a structured program needs to be set up and monitored. There is absolutely no point in starting something new if you don’t monitor it and review your results regularly. Without monitoring and review there is no way of assessing whether the program is effective, and that will inevitably lead to frustration and abandonment of a potentially helpful program. Involve your staff in gathering information and in choosing an appropriate program, then it’s far more likely to succeed.

If you find that your business is “too small” to consider such an idea, then form a cooperative with other small businesses in your area or within your trade, or contact the small business associations in your town or city. The small effort you put in will result in positive outcomes for you and ever bigger rewards for the wider community as time goes on.

Changing peoples patterns of life is a slow business. But if someone had told me of the huge changes that I’ve witnessed during the course of my medical career I probably wouldn’t have believed them. But I do believe that SMEs are the key to how we can change the health of our countries. And it only takes each of us to dare to do our little part, and then the resulting impact will be massive and long lasting.


Ampersands & angle brackets need to be encoded.

Tuesday, January 7, 2014

Away from my desk


But not totally away from all work.

The bride and I are enjoying a little Italian culture, which is why there haven't been any posts or podcasts recently.

But if you want some edifying reading, then click the link to my Blog on the HBF Website and see what I've been writing about over the Christmas/New Year period.

I wish you all a fantastic 2014, and I'll be back in thd saddle soon. Ciao.
Ampersands & angle brackets need to be encoded.

Wednesday, November 20, 2013

End of year student parties - more than just Memories.


The end of the College year and High School life means Celebrations with a capital "C". But the mixture of young people, hormones and alcohol can often leave them with more than just memories: Sexually Transmitted Diseases are amongst the most commonly reported infections across the globe.
In this Podcast I talk with Prof Donna Mak of the Communicable Diseases Centre in Perth, Western Australia about STDs and blood born virus infections.

I hope you enjoy.

Click HERE to download the Podcast

image
Ampersands & angle brackets need to be encoded.

Monday, November 11, 2013

Elvis and Immunization


Click HERE to download my Podcast with  Dr Paul Effler, MD, MPH, FAFPHM on childhood immunizations and why we mustn't become complacent.
Ampersands & angle brackets need to be encoded.

Friday, November 8, 2013

Cancer Council WA - Food labeling.


Click HERE to listen to my third talk in the Cancer Council WA series, where we discuss the food we eat, how to understand food labeling and what foods are good for us.

*my apologies for the quality of the sound: however, the quality of the advice is excellent!


image
Ampersands & angle brackets need to be encoded.